Breast Reduction
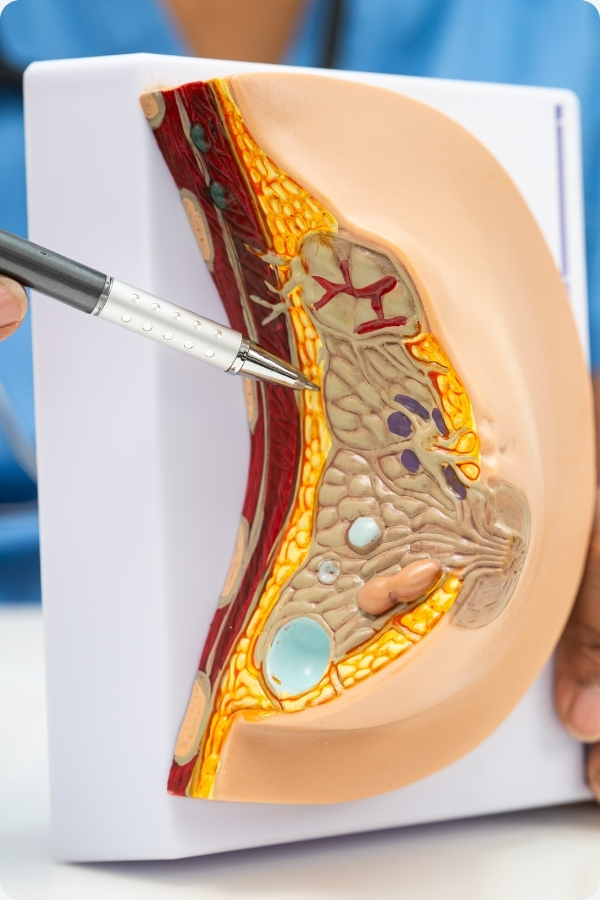
These are surgical procedures in which skin, fat, and breast tissue are removed to reshape the breasts, aiming to make large and sagging breasts smaller, firmer, and more upright.
Online Consultation
This is performed by our plastic surgeon.
Analysis & Planning
A personalized treatment plan is created in collaboration with our doctor.
Suitability
Our doctor will assess your suitability for the procedure.
Op. Dr. İlhan Serdaroğlu
I have been serving patients for over 25 years.
I graduated with honors from Marmara University Faculty of Medicine and completed my specialization in Plastic and Reconstructive Surgery at Akdeniz University. I believe that surgical experience, the selection of the right technique, and personalized planning are crucial in hair restoration. A natural, anatomically appropriate hairline design and a tissue-respecting surgical approach that reduces the risk of complications are essential in hair transplantation. While aiming to reduce the psychological effects of hair loss in both men and women, I also strive to apply medical and scientific supportive treatments and share my experiences globally.
HAIR TRANSFORMATION STARTS HERE.
You can plan your hair transplant process specifically for you by having an online consultation with Op. Dr. İlhan Serdaroğlu.
Contact us via WhatsApp, form, or phone.
Our expert team will provide preliminary information and schedule your appointment.
Plan your hair transplant with Op. Dr. İlhan Serdaroğlu.
OUR TREATMENT PROCESSES
Our patient processes at our clinic

Let us Call You
Who are suitable candidates for this surgery?
Due to genetic factors, hormonal changes, weight gain, or breastfeeding, an increase in breast tissue may occur, which can lead to large breasts that cause back pain and even a hunched posture. Irritation and rashes may develop under large breast tissue due to friction, and wounds may occur. Breathing difficulties may also be experienced. Daily physical activities may become limited. In addition, large breasts may create difficulties in choosing clothes, while dissatisfaction with one's appearance may lead to social and psychological problems. Therefore, such aesthetic operations can improve both the patient’s physical appearance and psychological well-being. This operation can be performed on any woman who has completed puberty and whose breast development is finished.
What should be considered when deciding on surgery?
Following the surgeon’s examination, the size and shape of the breasts, the condition of the skin, the patient’s age, marital status, plans for having children, and the new position and size of the nipple are discussed with the patient. As a result of this mutual exchange of information and dialogue, it is decided how and with which technique the operation will be performed and whether the nipple will be preserved.
Should a breast imaging test be done before surgery?
For surgery candidates above certain ages and for individuals with a family history of breast pathology, it is appropriate to perform a mammography examination and breast screening before the operation.
Under what type of anesthesia is the operation performed?
The operation is performed in hospitals under general anesthesia. Although patients may be able to stand up on the day of surgery, it is generally recommended that they spend their first night in the hospital.
What procedure is performed during the operation and what do the surgical scars look like?
The desired breast shape and size should be discussed between the surgeon and the patient. It is also important whether the patient plans to have children in the future in terms of breastfeeding function. In these operations, excess breast tissue and the overlying skin are removed. The nipple is moved to its appropriate position. Although many incision patterns can be used in breast surgery, the “Inverted T” incision is generally preferred. In this technique, incisions are made around the nipple, vertically from the lower edge of the nipple (at the 6 o’clock position) down to the breast fold, and along the breast fold itself. The breast is reshaped and closed in an “Inverted T” pattern. All of these scars are completely hidden by a bra. These permanent scars are usually very thin lines and are barely noticeable.
Breast reduction surgery can also be performed without making an incision along the breast fold. In some suitable cases, the reduction operation can even be performed through an incision only around the nipple.
Is a blood transfusion necessary during the surgery?
Blood transfusion is generally not required for breast reduction surgery. In cases where transfusion is necessary, the patient’s own blood collected 5–7 days before the operation can be used (autotransfusion).
How long does the reduction surgery take?
The operation usually takes between 2–4 hours, although in certain special circumstances the duration may be longer.
Will there be numbness in the nipple after surgery, and will breastfeeding function be lost?
In the early period, swelling, numbness, and bruising may occur in the nipple area. The numbness and bruising usually resolve within a short time. In these operations, since the nipple is repositioned by sliding without being completely detached and the milk ducts underneath are not cut, breastfeeding after childbirth is generally possible. However, in a special technique used for very large breasts, the nipple must be completely detached to achieve sufficient reduction. In such cases, permanent numbness in the nipple may occur after the operation. Naturally, breastfeeding is not possible in these cases because the milk ducts beneath the nipple are cut.
What should be considered after the operation?
The postoperative period is usually comfortable and pain is minimal. There may be some limitation in arm movements. Bandages similar to a bra are applied to the breasts, and a sports bra is worn for support. Usually, small tubes called “drains” are placed in both breasts and removed within 24–72 hours. Dressings are performed on the second or third day. Bruising and swelling may last for 2–3 weeks. Temporary numbness in the nipple and mild aching pain in the breast may occur after surgery. Generally, wearing a supportive bra for about 6 weeks and limiting arm activities for 2 weeks are recommended. It may take up to one year for the breasts to reach their final shape and for the scars to fade.
When can normal life be resumed?
- The patient can return to work after 1–2 weeks. It is recommended to avoid heavy sports activities for about 1.5 months.
Will the new breast shape remain permanent after breast reduction surgery?
The newly shaped breast generally maintains its form for a long time; however, weight changes, pregnancy, breastfeeding, and gravity may cause an increase in breast volume and lead to sagging again.
What are the possible unwanted results of breast reduction surgery?
As with any surgical procedure, complications such as infection, tissue loss due to poor blood supply at the wound site (especially in smokers and patients with diabetes), bleeding, and fluid accumulation in the breast (hematoma or seroma) may rarely occur after breast surgery. Minor leakage and crusting at the incision site are normal. Every surgical procedure heals with a scar, and the nature of the scars cannot always be predicted in advance. In some cases, scars may be barely noticeable, while in others scar tissue may develop within the skin and deeper tissues, sometimes requiring surgical correction or additional treatments. Hardness within the breast due to scar tissue or fat necrosis may rarely occur, and this cannot be predicted beforehand. Most women naturally have some degree of breast asymmetry. Very small differences in the shape, size, and symmetry of the breast and nipple may occur and are considered normal. In rare cases, local allergic reactions to adhesive tapes or suture materials may also develop.